

AJF Update
Kyoto Study Visit with Visitors from Australia
From May 29 to June 2, 2026, a five-day study visit was conducted in Kyoto and Nara together with six visitors from Australia, to learn about nurses working in primary health care and the systems supporting their practice. The visit included tours of multiple clinics and related organizations and served as a valuable opportunity to deepen understanding—from multiple perspectives—of community-based care in practice, the professional expertise of nurses, and the education, policy, and organizational structures that support it.
Day 1 — Friday, May 29, 2026
Participants gathered at 5:00 p.m. at a rental conference room in front of Kyoto Station and held a workshop on leadership and empowerment. Participants were divided into three groups based on different themes and held discussions. (Example themes: nursing autonomous practice / expansion of nursing practice such as prescribing rights and other discretionary authority; continuing education and workplace culture; human resources / workforce strategy; remote medicine/nursing; health issues of minorities such as immigrants, poverty, and youth.) Each group discussed the current situation, challenges, and potential solutions related to its theme. Beyond national and cultural boundaries, participants shared empathy for issues common to the nursing profession and considered solutions from their own individual perspectives.
 Outcomes of the group work
 Group photo with workshop participants
 Group work presentation
Days 2–3 — Saturday, May 30 to Sunday, May 31, 2026
Together with the Australian participants, the group attended the 17th Annual Conference of the Japan Primary Care Association, held at the Kyoto International Conference Center. At a symposium titled “Leadership in Action: Empowering Nurses in Primary Care – the Japan-Australia (APNA) Nursing Collaboration Project,” the group presented an overview of the project, challenges in primary care nursing in both countries, the organization and role of Australia’s primary health care nursing association, and the initiatives, challenges, and solutions being pursued by program participants as practitioners. Program participants who had taken part in online sessions also attended in person, and there were moments of deepened exchange through face-to-face interaction with the Australian participants.
 After the symposium
Day 4 — Monday, June 1, 2026
The group visited Tsuge Clinic, a municipal clinic in Nara City, Nara Prefecture. The journey from central Kyoto took about an hour and a half by expressway, including a stop to visit Todai-ji Temple in Nara along the way. Tsuge Village is now part of Nara City, having been merged into it about 20 years ago. It is a quiet farming area about 40 minutes from central Nara, known for rice and tea cultivation, with snowfall in winter and considerable seasonal temperature variation—and it is also an area experiencing progressive aging and a declining birthrate. Dr. Nishimura gave the group a tour of the clinic and carefully explained the clinic’s role in the community. Nurse Practitioner Suga spoke about the role of nurse practitioners, their engagement with local residents, and the importance of building and sustaining relationships. After the clinic tour, the group visited the home of a local resident who uses the clinic, who shared, from a resident’s perspective, how the clinic serves as a familiar presence and a foundation for everyday health management.
 In front of the entrance to Tsuge Clinic

Participants listening to an explanation from the nurse practitioner
Day 5 — Tuesday, June 2, 2026
The group returned to Kyoto, where the morning was spent in an information exchange session on community nurse activities (explanation to be added). Rather than the traditional definition of delivering care to those in need in a community, community nursing here refers to activities that promote and maintain people’s well-being and health as an extension of community activities that become part of people’s daily lives. The group heard from [XX], who carries out such activities based in Kyoto. Participants found it interesting to reconsider residents’ health from a new perspective and to shift their thinking in this way. They reaffirmed the need to consider, both within Japan and in rural Australia, how to leverage regional characteristics to support community health and disease management systems—including the sustainability of maintaining such systems.
 Information exchange session on community nurse activities
In the afternoon, the group visited Tahara Clinic near Iwakura Station. Located just by Iwakura Station in the northeast of Kyoto City, the clinic sits in what is described as a rural corner of Kyoto, surrounded by rice paddies and the flowing waters of the Iwakura River—a quiet area that is nonetheless geographically convenient for transportation. The area sees snowfall and considerable cold in winter, has a relatively large number of school facilities, and a comparatively large child population. Director Dr. Tahara explained the characteristics of the area and an overview of the clinic’s patient population, after which the group toured the clinic. Participants were surprised to find familiar equipment and medications while also noting differences in how they are used—in particular, that Japanese clinics are almost always equipped with X-ray machines and often even CT scanners. Participants also found it novel that, unlike in Japan where patients can go directly to a specialist, in Australia GPs serve as the first point of access to medical care in the community, which shapes how care is divided among nearby specialists. Discussion was also lively around the detailed nursing care provided by clinic nurses and the ingenuity used to run clinical operations smoothly—a theme common to both countries.
 Participants listening closely to a nurse’s explanation of medications
 The clinic director explaining the clinic
 Commemorative photo with participants
Discussion and Summary
The five-day program moved from an educational workshop (Day 1) to presentations at the academic conference (Days 2–3) to a visit to a rural/remote clinic (Day 4) to visits to an urban clinic and a community care initiative (Day 5). Rather than a simple series of facility tours, this structure offered an opportunity to compare Japanese and Australian nursing practice on multiple levels and to learn from one another. For the Japanese participants in particular, this comparative perspective may have been sharpened by their earlier study visit to Melbourne in February 2026, which gave them an additional point of reference. Through the actual site visits and interviews, the discussion of nurses’ roles in primary care could be said to have deepened around the following points.
References to the “building and sustaining of relationships” between nurse practitioners and local residents echoed the workshop theme of expanded discretionary authority for Australian primary care nurses, such as prescribing rights, suggesting a contrast with the more limited scope of authority under Japan’s nurse practitioner system. This contrast, however, was not explicitly discussed within the report itself and remains a topic for further consideration.
The difference between the Australian system observed at Tahara Clinic, in which GPs serve as the first point of access to care, and the Japanese system, in which patients can consult specialists directly, reflects a structural difference in healthcare systems—namely, the presence or absence of a gatekeeping function. However, the report does not analyze how this difference affects the differing roles of primary care nurses in each country.
Through the explanation of community nursing as a nursing approach that departs from its “traditional definition,” participants may have been exposed to a new perspective on how such an approach is implemented in the community. How this new approach, or framework, might connect with community-based integrated care in Japan remains a subject for future consideration. It is also hoped that Australia will, going forward, take into account evolving forms of community-based nursing and care, and that this will lead to further information exchange and social implementation within primary care nursing in both countries.
We Conducted a Study Tour in Melbourne.
From February 16, 2026, for three days, we conducted a study tour of several clinics and related organizations in Melbourne, Australia, to learn about nurses working in primary healthcare and the systems within their practice settings. This tour provided a valuable opportunity to deepen our understanding from multiple perspectives regarding the realities of community-based care, the exercise of nursing expertise, and the nature of the education, policies, and organizational structures that support them.
Day 1: Medical One Clinic
On the first day of the study tour, we visited a clinic in Waurn Ponds, a suburb located about an hour by train from Melbourne central. We were welcomed by the nurse manager at a stylish, spacious facility that included a triage room, examination rooms, and a laboratory, with rehabilitation and podiatry (foot care) services also on-site. While enjoying the traditional Australian “Morning Tea,” we received an overview of the Australian healthcare system—including how GPs act as gatekeepers, managing common illnesses, providing ongoing care for chronic conditions, and referring patients to specialists—as well as an explanation of the clinic’s services (Medical One is a group that operates General Practice clinics in the suburbs of Melbourne and Sydney).
 Picture: At the entrance to Medical One
 Picture: Overview of Medical One
 Picture: Morning tea
The clinic employs 10 doctors and 3 nurses. The nurses play specialized roles across a wide range of tasks, including triage, chronic disease management (nursing outpatient services), vaccinations, iron infusion therapy, and wound care. Vaccinations, which are a primary service, are managed through a shared online registration system, and nurses administer them under the supervision of doctors.
What was particularly striking was a scene regarding vaccination record books: when asking not only parents but also a 5-year-old preschooler for permission to show the record book to the visitors, we truly felt that “patient-centered care” is deeply ingrained in their daily practice. We also observed firsthand how women’s health is widely practiced within primary care, including the widespread administration of iron IV drips for iron-deficiency anemia—primarily among adolescent females—and the practice of contraceptive implant insertions performed by nurses certified in the technique.

Many clinics also provide chronic wound care. On the day of my visit, a Convatec Wound Specialist presented updates on wound care, including guidelines from the International Wound Infection Institute regarding chronic wounds and wound debridement, as well as a product demonstration of Aquacel AG. It was impressive to see how, with this external educational support, nursing staff were providing meticulous, guideline-based care.

We also had the opportunity to hear from a representative of the Primary Health Network (PHN) [1] about their role and collaboration with clinics. The PHN is an independent organization established in 31 regions nationwide with the aim of improving the quality of primary care in each area. It is responsible for assessing local health needs, coordinating with related organizations such as the APNA, creating and managing the quality of necessary services, and supporting the education and quality improvement activities of healthcare professionals. It was explained that the PHN works closely with each clinic; for the clinic we visited, this included providing data-driven evaluations and feedback, as well as promoting women’s health through quality improvement initiatives such as screening for menopausal symptoms.
[1] Reference site: https://www.health.gov.au/our-work/phn/what-PHNs-are

Day 2: Summerhill Medical Center
Located in a shopping center about an hour by train from central Melbourne, the clinic features a large sign at the front reading “Bulk Billing” (direct billing to Medicare, no out-of-pocket costs), and is characterized by its accessibility, including its convenient location.
We received an explanation of the “chronic disease management” program from the head nurse, who has worked at the clinic for many years. This program targets patients with symptoms lasting six months or longer and involves multidisciplinary intervention led by a GP, with costs covered by Medicare. Nurses used a standardized format—“Problem, Goal, Actions to Achieve the Goal”, “Support Needed to Achieve the Goal”—to create comprehensive care plans. This clearly demonstrated a “patient-centered” approach to healthcare, where the individual takes the lead in deciding their own health and care, and healthcare professionals provide support. Based on this care plan, the clinic conducts patient education, referrals to other departments and rehabilitation services, health maintenance activities such as cancer screening, and comprehensive health assessments that include psychological aspects.
While meticulous assessments and care plans were being developed, challenges included the fact that the nursing outpatient visits took just under an hour, making it difficult to balance them with other duties; the requirement to bill under the physician’s name; and the need for training for new nurses. This reaffirmed the importance of organizational management in enabling professionals to fully utilize their capabilities.
Furthermore, regarding the clinic’s location, it was noted that many patients have diverse backgrounds (ethnicity, language, etc.), highlighting the importance of explanations using easy-to-understand language and diagrams, as well as communication that takes cultural backgrounds into account. This was particularly insightful for the Japanese healthcare system, where the number of patients with foreign roots is increasing. APNA offers a six-month educational program on chronic disease management, and its implementation is reportedly expanding across Australia.
 Picture: Gathering in front of the clinic
Furthermore, as part of the clinic’s quality improvement initiatives, nurses monitored quality indicators, such as whether social background factors like alcohol consumption and smoking were documented in patient records and whether appropriate diagnostic codes were recorded. Data demonstrated that these indicators improved when healthcare professionals, led by nurses, conducted assessments, serving as evidence of the nursing outpatient clinic’s effectiveness. Other activities included updating practice support guidelines in line with updated clinical guidelines, providing explanations of new medications, creating and reviewing facility and operational regulations and procedures, and conducting in-house education that included non-medical staff.
Additionally, they collaborated with universities to participate in cohort studies on dementia and research on COPD management. The head nurse, who oversees these diverse activities, stated, “There are many nurses working in primary care, and if they can effectively handle palliative care and mental health, the quality of primary care will certainly improve. Education, particularly through organizations like APNA, is crucial. Furthermore, the nursing profession has not sufficiently communicated our practice to the outside world. It is vital that we clearly convey our daily practice and its effects—both economic and on patient health.”
Australian Primary Healthcare Nurse Association (APNA)
On the evening of the second day, we visited the APNA office. We were told that APNA, as a professional organization advocating for nurses engaged in primary healthcare across Australia, is involved in continuing education, policy advocacy, collaboration with related organizations, and public relations.
A visitor from Japan asked, “How can nurses continue their continuing education autonomously (with motivation)?” The response was: “As professionals, nurses are expected to enhance their knowledge and skills to provide high-quality healthcare. While this attitude is a professional standard required of all nurses, many only realize its necessity several years after beginning their practice. At that point, APNA actively communicates through public relations and events (such as the Festival of Nursing) just how important a role nurses play.” In fact, the posters and magazines produced by APNA depict nurses practicing their work with confidence and vitality, as well as how nursing practices in various regions are solving residents’ health challenges, thereby motivating and empowering nurses on the front lines.
Regarding this study tour, the website also highlights the mutual learning that took place through interactions among the participants.
Furthermore, at the clinics visited, a system was in place where nursing staff acquired the knowledge and skills required for on-site practices—such as contraceptive implant insertion, vaccinations, and chronic disease management—through training programs and other initiatives and received certification. This ensured the safety and quality of care while also enhancing the sense of fulfillment among nursing staff. In response to a question from the visitors asking, “How do you ensure the quality of continuing education (knowledge and skills)?” the free app “Florence,” provided by APNA as part of its continuing education and career development support, was introduced. Based on the career education framework, it enables users to set goals, select appropriate programs, and track and visualize their progress.
Furthermore, citing the annual survey of nursing practice, it was noted that current practice does not fully reflect nurses’ capabilities. Policy recommendations are being made to expand the scope of practice, such as prescribing medications. Additionally, by fostering collaborative relationships not only with nursing but also with related organizations such as pharmacists and rehabilitation professionals, the nursing profession can form a stronger, unified “voice.” This was illustrated using the example of the report “Unleashing Potential of our health workforce” compiled by the government last year.
 Picture: At the APNA reception desk
Day 3: Spring Medical Clinic
On the final day, we drove for an hour and a half through grassland to visit the Spring Medical Clinic in Daylesford, a town famous for its hot springs and organic farming. The spacious building was decorated with drawings by local children, creating a colorful and cheerful atmosphere. The clinic is conducting an intervention study titled “Practice Nurses to Augment the Clinical Evaluation and Care of People at High Risk of Heart Failure” (PANACEA-HF), which includes early screening for heart failure by nurses using AI-enabled echocardiography. We received an explanation of the screening process from the nurse in charge and observed an actual echocardiography examination. The results of this study are scheduled to be presented at academic conferences in the future, and we were told that the global community is paying close attention to the effectiveness of preventive interventions for heart failure.
In the wound care department, we were able to speak with actual patients and observe how residents have built trusting relationships with the nurses, ensuring the provision of continuous care. It was striking to see how the staff we met were working with such a sense of fulfillment and vitality. When the visitors asked the manager how they maintain this joyful atmosphere and high motivation, he replied, “We create many opportunities to show our appreciation for the staff, and we try to celebrate occasions like birthdays together as much as possible.” It was a highly educational visit that highlighted how to create a workplace where every single staff member feels valued.
 Picture: With the clinic manager and staff
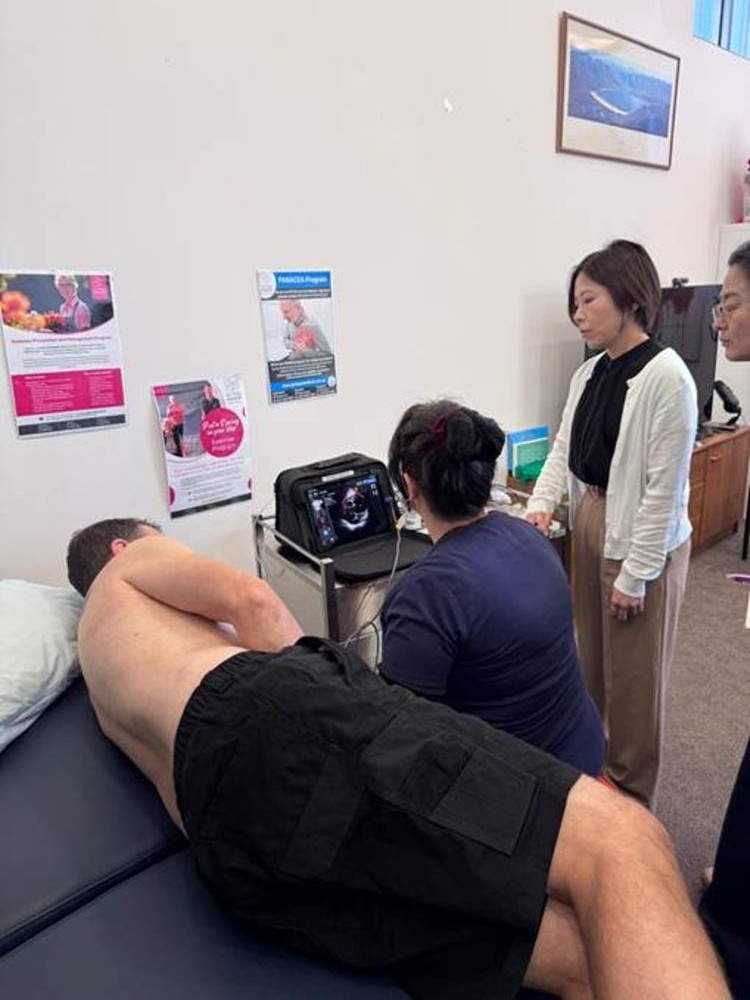 Picture: Demonstration using AI-powered echocardiography
Young People’s Health Service
On the afternoon of the final day, we visited a program designed to support young people aged 12 to 24 who have nowhere to go due to financial hardship, domestic violence, or social exclusion, and who require medical care, daily living support, and accommodation. Upon entering the easily accessible building located in central Melbourne near a major train station, we noticed that all staff were dressed in casual attire, and the interior had a very casual and bright atmosphere.
The accommodation floor featured several rooms arranged around a cozy lounge, along with dedicated spaces for activities such as music and cooking. At this facility, a team of three nurse practitioners provided primary care—including vaccinations, health assessments, mental health services, and sexual health care. As an affiliate of the Royal Children’s Hospital, the program connects clients to specialized care when necessary. In terms of social support, social workers lead efforts such as employment counseling and support for independent living.
Although the facility is operated with public funding from the government, we were told that there is a shortage of accommodation units. This program also conducts outreach in the Melbourne area once every two weeks at a satellite site, and interpreters are available to provide support in the young people’s native languages when necessary, ensuring a system that is easily accessible to them.

Summary
Through this study tour, I learned that nurses in primary care do not limit themselves to clinical practice but play diverse roles—including chronic disease management, prevention, education, improving the quality of care, research, and policy advocacy—and demonstrate leadership. Furthermore, I was deeply impressed by the fact that professional associations like the APNA provide strong support to nurses working in the field, as continuing education, data utilization, organizational support, and advocacy as professionals are essential for practices that fully leverage the expertise of nursing professionals. Furthermore, the insights gained during this study tour—including the promotion of patient autonomy, workplace empowerment, and approaches to underserved populations—provided important implications for the development of primary care nursing in Japan.
We are awarded Australia Japan Foundation!
The project title is Leadership in Action: Empowering Nurses in Primary Care. The program aims to strengthen leadership and advocacy for the roles of participants in their respective positions by providing a collaborative design (co-design) program for nurses in Australia and Japan, particularly those working in primary care, through professional exchange. By developing the program in consultation and collaboration with participating nurses and stakeholders working in primary care in Japan and Australia, it aims to increase recognition of the vital role nurses play in community nursing. Participants in the primary care nursing program will reaffirm their own roles and circumstances. Through the program, they will understand their individual leadership and plan future action plans. Updates on activities will be provided as they become available. Stay tuned!
Our program partner, Australian Primary Health Care Nurses Association (APNA) share the news on their website.
APNA welcomes Japan Australia collaboration grant funding
Press release from Australia Japan Fund
Australia-Japan Foundation grants recipients 2025-26 | Australian Minister for Foreign Affairs
